Skip to content

Free delivery on orders over €350. Fast delivery.

Search

What are you looking for?

Type at least 2 characters to see suggestions.

L-Carnitine 400 mg/1 ml - 10 ml

L-Carnitine 400 mg/1 ml – 10 ml

L-carnitine (L-carnitine, levocarnitine) 400 mg/ml — sterile solution for intramuscular injection in a single 10 ml vial (4000 mg), purity ≥98% HPLC, MS confirmation, COA per batch. Standard variant in the injection family: carnitine shuttle transport molecule (CPT1/CPT2) supporting fat transport to the mitochondrion and post-exercise regeneration. Bioavailability i.m. ~100% bypasses the oral absorption barrier.

47,99 €
Fast shipping
Delivery options Free delivery from 350 €
Returns policy
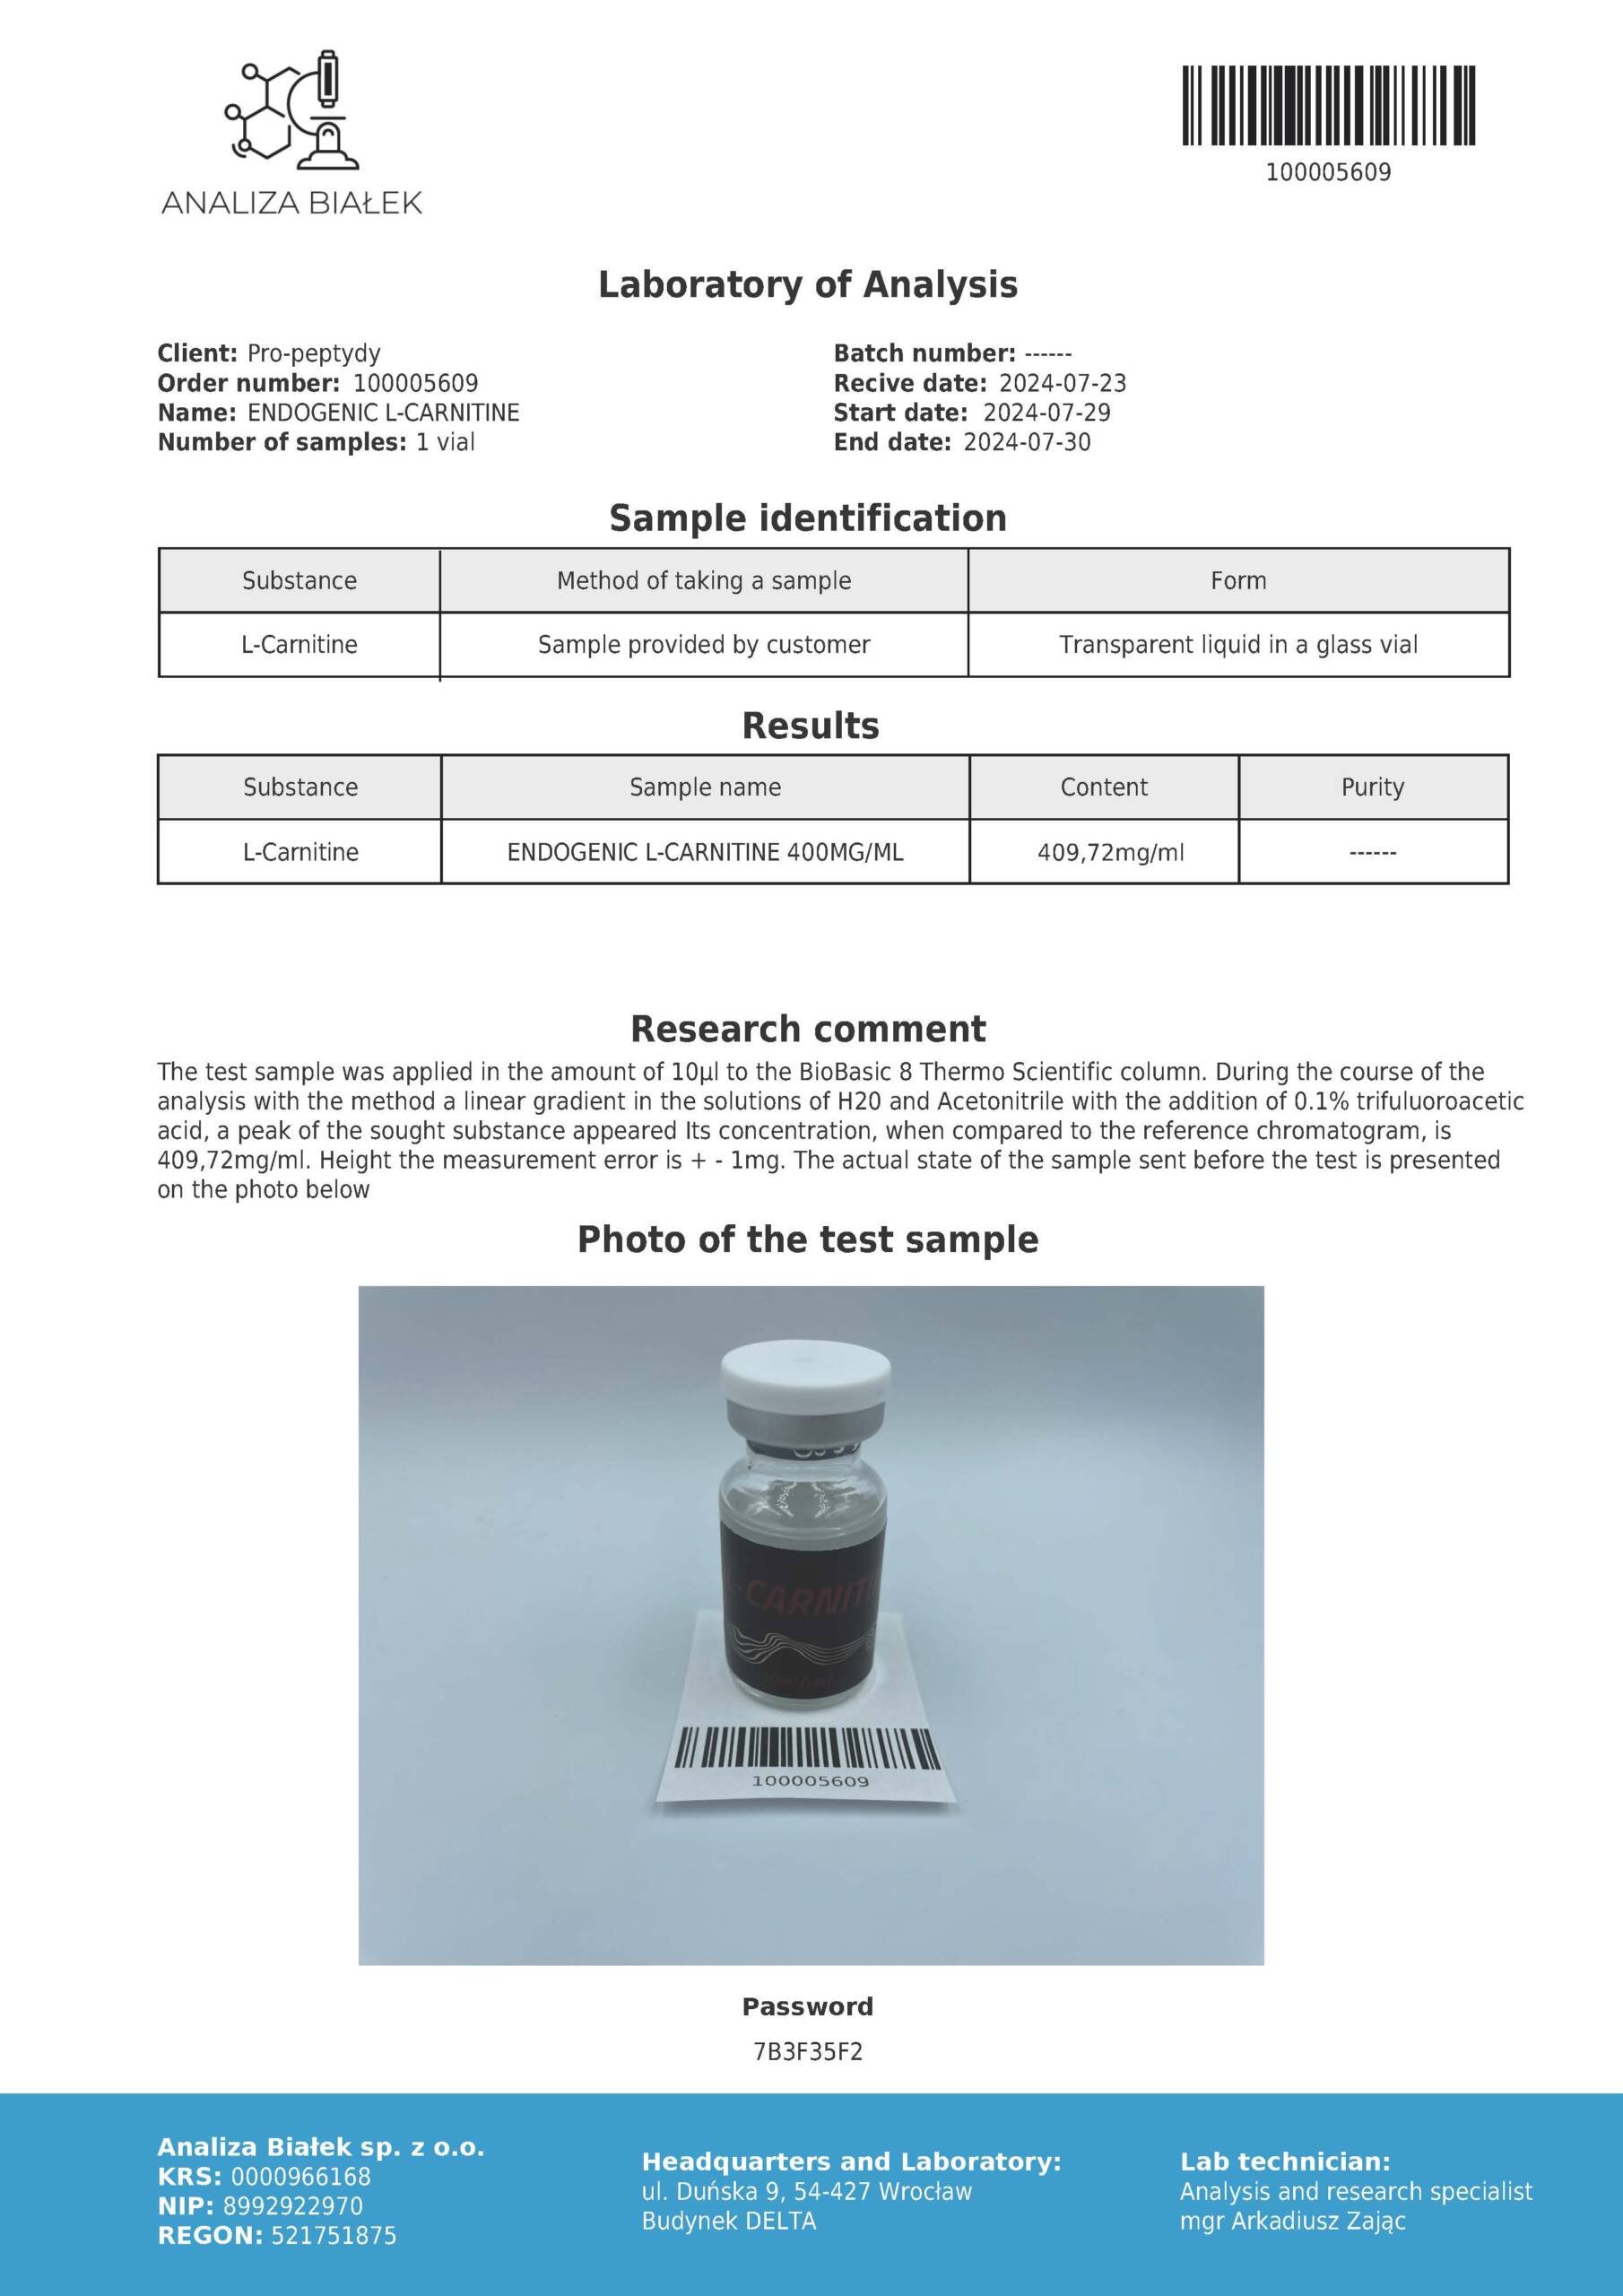
View the laboratory analysis report

L-Carnitine 400 mg/ml - injection solution

  • L-carnitine (levocarnitine): concentration of 400 mg/ml.
  • Single 10 ml vial containing 4,000 mg of L-carnitine in total.
  • Product characteristics, contraindications and legal status are described below.

Product status information

A specialized sports preparation in injection form, intended only for adults (21+), for self-assessment of risk. L-carnitine in oral form is an EFSA-assessed ingredient, however solution for intramuscular injection is not a dietary supplement in the Polish and EU legal sense. Before making any decision, please read the “Legal Status” section and contraindications at the end of the description.

WARNING – WADA, CATEGORY M2.2 (prohibited methods)

Intravenous and intramuscular administration of L-carnitine is subject to World Anti-Doping Agency category restrictions M2.2 – chemical and physical manipulations (intravenous/intramuscular injections above 100 ml in a 12-hour period). Injectable L-carnitine is not a prohibited substance per se, but route of administration and volume may violate anti-doping rules. Registered athletes (ADAMS) must check the current list of prohibited methods and volume thresholds before making any decision regarding use. If in doubt, consult the anti-doping organization appropriate for your sport.

Introduction

L-carnitine is one of the best-studied molecules in exercise physiology – and one of the most misunderstood. In its oral form, it fights the bioavailability barrier: a 2-gram tablet translates into several percent of the actually absorbed molecule, and saturation of the muscle pool by oral route requires weeks of daily administration and the presence of insulin as an “elevator” transporting carnitine into the muscle cell (Stephens et al. 2007).

It is this pharmacokinetic obstacle that makes advanced athletes use the injectable form – intramuscular administration bypasses the digestive tract and the first passage through the liver, delivering virtually the entire contents of the vial into the circulation. This preparation is 400 mg/ml solution in a single 10 ml vial (total 4000 mg L-carnitine). A concentration of 400 mg/ml is standard, middle variant in the L-carnitine injection family – stronger than the gentle version L-Carnitine 200mg and milder than the concentrated variant L-Carnitine 600mg.

In practice, 1 ml of solution corresponds to 400 mg of pure molecule: the starting dose is 1 ml (400 mg), the standard range is 1.5–2 ml (600–800 mg), and the upper limit of a single administration is 5 ml (2000 mg). A single 10 ml vial is natural entering the protocol before deciding to purchase the set — allows you to complete a full mini-cycle of tolerance assessment without committing your budget to a multi-vial package.

L-carnitine is not a stimulant and does not work “from the first administration” like a pre-workout supplement. Its role is metabolic and cumulative: it increases the pool of molecules available for the transport of fatty acids to the mitochondria, buffers the pool of free coenzyme A and supports regenerative processes after exercise (Volek et al. 2002, Wall et al. 2011).

Coach Marek would put it this way: it’s a tool for the patient – you work on the muscle pool throughout the entire cycle, not on a single energy kick.

Mechanism of action at the molecular level

L-carnitine serves as a transport molecule in one of the central energy pathways of the cell – the carnitine shuttle, which shuttles long-chain fatty acids across the inner mitochondrial membrane. Without it, fat simply will not go where it is burned.

Fatty acid transport – CPT1/CPT2 system

Long-chain fatty acids do not cross the inner mitochondrial membrane on their own. Enzyme on the outer membrane carnitine palmitoyltransferase I (CPT1) combines the fatty acid acyl residue with carnitine to form acylcarnitine. This form is transported to the mitochondrial matrix, where carnitine palmitoyltransferase II (CPT2) detaches carnitine and releases acyl-CoA ready for oxidation. Carnitine flows back out and the cycle repeats. This pendulum is the bottleneck of β-oxidation – the larger the pool of available carnitine, the more efficiently the fat substrate is transported (Karlic and Lohninger 2004).

Beta-oxidation – releasing energy from fat

Once acyl-CoA is delivered to the mitochondrial matrix it begins β-oxidation — a spiral sequence of reactions cutting off two-carbon fragments of acetyl-CoA from the fatty acid chain, which power the Krebs cycle and the respiratory chain. Carnitine does not participate in β-oxidation itself, but it determines the supply of substrate to it. In the context of sports, this translates into more efficient use of fat as fuel during moderate-intensity exercise – which, with an appropriate caloric deficit, supports the reduction of body fat.

Buffering the pool of free coenzyme A

The second, often overlooked function of carnitine is buffering the ratio of acyl-CoA to free CoA. During intense exercise, when glycolysis accelerates, acetyl-CoA accumulates in the mitochondrial matrix and the pool of free coenzyme A decreases. Carnitine takes over excess acetyl residues, creating acetylcarnitine and restoring free CoA, necessary for further work of pyruvate dehydrogenase. This mechanism slows the accumulation of lactate and supports maintaining the rate of aerobic metabolism with increasing intensity (Stephens et al. 2007).

Supporting regeneration and limiting post-exercise damage

Volek and colleagues (2002) showed that L-carnitine supplementation reduced markers of muscle damage and oxidative stress after resistance exercise and reduced the subjective sensation of muscle pain (DOMS). The mechanism involves improving blood flow in the muscle, reducing tissue hypoxia and reducing damage to cell membranes by free radicals. For the advanced athlete, this means a shorter recovery time between heavy units.

Impact on endurance and exercise economy

Wall et al. (2011) in an elegant study with 24-week supplementation showed that chronic administration of L-carnitine (with co-supply of carbohydrates) increased the carnitine content in the muscle by approximately 21%, which translated into glycogen sparing at lower intensity and lower lactate accumulation and higher power output during high-intensity exercise. This is one of the few studies that actually documented the saturation of the muscle pool in humans and linked it with a measurable improvement in exercise parameters.

SCIENTIFIC PERSPECTIVE

Most of the strong evidence for L-carnitine comes from oral studies with carbohydrate co-supply (Stephens 2007, Wall 2011). The injection form bypasses the barrier of oral bioavailability, but there is significantly less direct research on intramuscular administration of L-carnitine in athletes than oral data. The fat transport mechanism (CPT1/CPT2, β-oxidation) is well established; the transfer of benefits from an oral to an injectable protocol is based mainly on pharmacokinetic reasons (higher bioavailability) and not on large clinical trials with the injectable form.

Positioning of the 400 mg/ml variant - when to use this one and when to use another one

Injectable L-carnitine comes in three concentrations that differ in the volume needed to administer the same dose and the comfort of injection:

  • 200 mg/ml (gentle): the largest volume at a given dose, the gentlest on the tissue, a good entry point for people sensitive to injection pain or taking their first steps with the injectable form.
  • 400 mg/ml (standard – this preparation): golden mean. The standard dose of 600–800 mg falls within a comfortable 1.5–2 ml, with an upper limit of 2000 mg in 5 ml. The most universal choice for most advanced users in the reduction phase.
  • 600 mg/ml (concentrated): the smallest volume at a given dose, for people who have already developed injection tolerance and want to limit the injection volume.

If you are just starting to inject L-carnitine and don’t know how your tissue will react, a single vial of 400 mg/ml is the most reasonable starting choice. A broader context of selecting lipolytic agents in the cut phase is discussed in the guide effective fat burners. Check the availability of a single vial in the store, complete a mini-cycle of tolerance assessment, and after a positive decision, upgrade to a package with better economics: set 3x L-Carnitine 400mg (+1 free).

Safety rules

L-carnitine belongs to molecules with a good tolerance profile, but the injection form introduces additional risks related to the route of administration itself. The following rules are of an orderly nature, not of a medical nature.

Pain and local reactions at the injection site

Intramuscular administration of a 400 mg/ml solution may be associated with transient pain, burning or redness at the injection site. To reduce discomfort: use a sterile technique, rotate injection sites, warm the vial to body temperature before administration, and divide larger volumes between two sites. Persistent redness, swelling or fever requires medical attention.

TMA/TMAO – metabolic pathway for conscious observation

Carnitine is metabolized by intestinal bacteria into trimethylamine (TMA), which is oxidized in the liver to Trimethylamine N-oxide (TMAO) — association with cardiovascular risk in observational studies (Koeth et al. 2013). This pathway mainly involves chronic oral intake dependent on the intestinal microbiota; the injection form bypasses the gastrointestinal tract, which theoretically limits intestinal conversion, but does not eliminate hepatic metabolism. People who care about their cardiovascular profile should keep this mechanism in mind and maintain cyclical, not continuous use.

Kidneys, thyroid and drug interactions

  • Kidney failure: carnitine elimination is mainly renal – advanced renal failure is a contraindication.
  • Thyroid: L-carnitine may weaken the peripheral effects of thyroid hormones (acts as a peripheral antagonist) – people with hypothyroidism or treated with levothyroxine should be careful and monitor the symptoms.
  • Coumarin (anticoagulants): Intensification of the effect of oral anticoagulants (acenocoumarol, warfarin) by L-carnitine has been reported, which may prolong the prothrombin time (INR). Combining requires INR control and medical consultation.

Other rules

  • Use only sterile injection technique and disposable equipment
  • Do not exceed 5 ml (2000 mg) per single administration
  • Cyclical use (4-8 weeks), not continuous
  • Hydration supports the renal elimination of the molecule
  • Please note WADA injection restrictions (Category M2.2) – see warning at the beginning of the description

Absolute contraindications

  • Pregnancy and breastfeeding
  • Age under 21
  • Advanced kidney failure
  • Epilepsy (decreased seizure threshold has been reported at high doses)
  • Current treatment with oral anticoagulants (coumarins) without supervision and INR control
  • Known hypersensitivity to L-carnitine

Legal status

The status of injectable L-carnitine requires the distinction of two distinct frameworks: the oral form (evaluated through food) and the injectable form (outside the dietary supplement framework).

  • Oral form – EFSA: L-carnitine as an oral ingredient is known to food evaluation authorities; EFSA (The European Food Safety Authority) analyzed health claims regarding L-carnitine in the context of fat metabolism – however, no health claims regarding “fat burning” were authorized as an approved health claim. The oral form is marketed as an ingredient of dietary supplements under food regulations.
  • Injection form – outside the supplement frame: solution for intramuscular injection is not a dietary supplement in the Polish and EU legal sense. Parenteral administration (injection) falls outside the definition of a food. We classify this preparation as: specialized sports preparation in injection form for adults (21+), for your own risk assessment.
  • GIS: The Chief Sanitary Inspectorate (GIS) does not classify the injection form as a permitted food ingredient/supplement – the preparation functions outside the framework of a dietary supplement as a product for advanced athletes.
  • WADA – Category M2.2: L-carnitine itself it is not a prohibited substance, But intravenous and intramuscular administration subject to limitations within the method M2.2 – chemical and physical manipulations (injection volume limit: 100 ml in a 12-hour period, excluding justified hospital treatment). Registered athletes (ADAMS) must verify the current list of prohibited methods and volume thresholds before making any decision regarding use.

The preparation is intended only for adults (21+) to independently assess the risk. Communication of the product as a medicine, as a registered “fat burning” product or as a dietary supplement in injectable form is unacceptable.

Summary

L-carnitine (levocarnitine, CAS 541-15-1, C₇H₁₅NO₃, 161.20 g/mol) is a quaternary ammonium derivative acting as a transport molecule in the carnitine shuttle: through the CPT1/CPT2 system, it transports long-chain fatty acids across the mitochondrial membrane for β-oxidation, buffers the pool of free coenzyme A and supports post-exercise regeneration (Karlic and Lohninger 2004, Volek et al. 2002).

The injection form bypasses the oral bioavailability barrier (~100% i.m. bioavailability), which makes it an advanced tool in the body reduction phase. Wall et al. (2011) documented saturation of the muscle pool and improvement of exercise parameters with chronic administration. This preparation is a solution 400 mg/ml – standard variant – In single vial of 10 ml (4000 mg), purity ≥98% HPLC, MS confirmation, COA per batch.

The dose is regulated by volume: 1 ml is 400 mg (start), 1.5–2 ml is 600–800 mg (standard), 5 ml is 2000 mg (maximum). The single vial is the entry into the protocol before deciding on the kit. Injection is subject to WADA M2.2 restrictions.

Bibliography

  1. Stephens FB, Constantin-Teodosiu D, Greenhaff PL (2007). New insights concerning the role of carnitine in the regulation of fuel metabolism in skeletal muscle. PubMed
  2. Wall BT, Stephens FB, Constantin-Teodosiu D, Marimuthu K, Macdonald IA, Greenhaff PL (2011). Chronic oral ingestion of L-carnitine and carbohydrate increases muscle carnitine content and alters muscle fuel metabolism during exercise in humans. PubMed
  3. Volek JS, Kraemer WJ, Rubin MR, Gómez AL, Ratamess NA, Gaynor P (2002). L-Carnitine L-tartrate supplementation favorably affects markers of recovery from exercise stress. PubMed
  4. Karlic H, Lohninger A (2004). Supplementation of L-carnitine in athletes: does it make sense?. PubMed
  5. Pekala J, Patkowska-Sokoła B, Bodkowski R, Jamroz D, Nowakowski P, Lochyński S (2011). L-carnitine — metabolic functions and meaning in human life. PubMed